

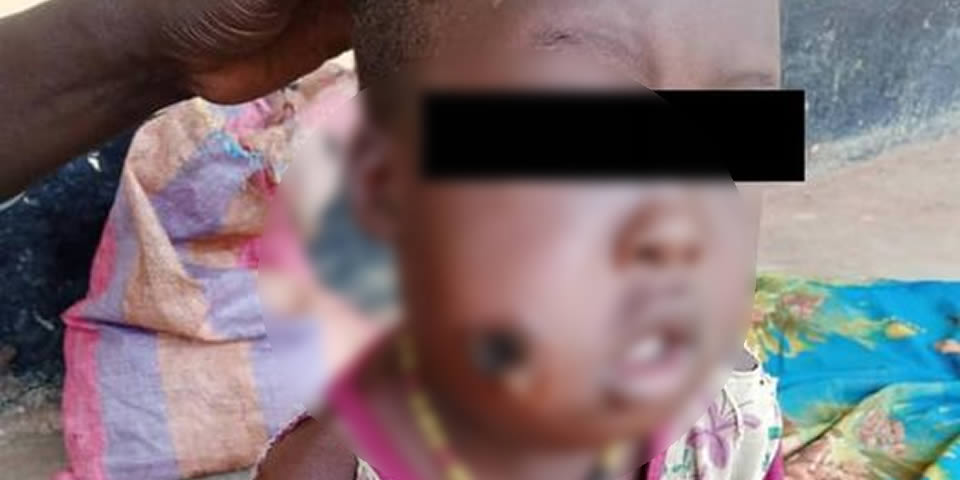
Cutaneous Anthrax is an infection of the skin. It comes about when the spores of the anthrax bacteria (Bacillus anthracis) get into the skin through a cut or a scrape. It typically forms a painless sore/ulcer with a black center known as an eschar that can be on the face, neck or arms.
It is more common in animals, however, human infection is rare but may sometime occur. Predisposing factors include coming into contact with infected animals or their products. Human animal interaction is quite common in South Sudan as many communities are primarily cattle herders.
Antibiotics like penicillin are usually effective in treatment but treatment must be started early after exposure.
Picture used with permission, courtesy of Dr. Deng Ezekiel.
Photo identity – 10yrs old, female with Right cheek Cutaneous Anthrax at Kuacjok State Hospital, Warrap State, South Sudan.
Further Details on Cutaneous Anthrax by Dr. Deng Ezekiel
Clinical Features of Cutaneous Anthrax
1. Starts after inoculation of spores into skin
2. Incubation period of 5-7 days(1-12days)
3. The infection starts as small painless pruritic papule, that discharges clear to light greenish fluid
4. The papule may enlarge into a bulla – which erodes within 2-6 days, leaving a necrotic black depressed center(eschar) with extensively edematous and hyperaemic surrounding tissues( hallmark of cutaneous anthrax)
5. Regional Lymphadenopathy and Lymphangitis is also associated with c. Anthrax.
6. 90 -95% of cutaneous anthrax occurs in exposed areas( face, neck, arms, hands)
Treatment
1. Fluoroquinolone are considered first line antibiotics in areas where sensitivity to Penicillin are not known or has not been demonstrated. Dose of Ciprofloxacin IV is 30mg/kg/day divided into (2- 3 doses) ( bactericidal)
2. If there is extensive edema involving the face or neck, admit the patient for to the hospital
3. If there is systemic involvement or extensive edema of head or neck add protein synthesis inhibitor antibiotics
4. Clindamycin is the most preferred protein-synthesis inhibitor, doxycycline, linezolid, rifampicin are preferred alternatives
5. Watch out for systemic symptoms; fever, fast breathing, hypotension, abdominal pain (abdominal spread)
6. Isolate anthrax patients
7. Adjunctive glucocorticoid therapy is controversial, but can be used in extensively edematous cases, especially on the face, neck